
Why Technique, Not Technology, Determines Clinical Value
Musculoskeletal ultrasound has become increasingly accessible in sports medicine and rehabilitation settings. Portable systems are more affordable than ever, image quality continues to improve, and more clinicians are integrating ultrasound into daily practice.
But access alone does not equal accuracy.
In real-world clinical environments - sidelines, training rooms, busy outpatient clinics - the value of muscle ultrasound depends far less on the machine and far more on how the scan is performed and why it is being performed.
This article outlines a practical, evidence-informed framework for performing muscle ultrasound scans with clinical purpose, consistency, and confidence.
The Problem: “Cool Images” Without Clinical Context
Many clinicians begin ultrasound training focused on image appearance:
How clear is the image?
Are the fascicles visible?
Does it look like the textbook?
While image quality matters, a visually appealing image does not guarantee a clinically meaningful scan.
Common pitfalls we see in practice include:
Spot-scanning only the area of pain
Inconsistent patient positioning
Poor probe angle leading to anisotropy
Skipping dynamic assessment
No contralateral comparison
These issues can lead to missed pathology, overinterpretation of normal variants, or false reassurance during rehab and return-to-play (RTP) decisions.
Muscle Ultrasound Is a Process, Not a Snapshot
High-quality muscle ultrasound follows a structured scanning process, not a single frozen image.
A systematic approach allows clinicians to:
Reduce operator-dependent variability
Identify subtle MTJ and intramuscular pathology
Monitor healing and remodeling over time
Contextualize imaging findings with function
Below is the framework we emphasize in our RMSK ultrasound education.
Step 1: Patient Positioning Sets the Foundation
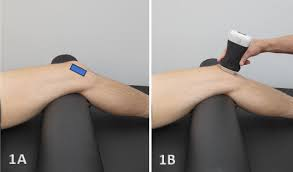
Proper positioning optimizes fiber orientation, tension, and image consistency.
Examples:
Quadriceps: Supine, knee relaxed or slightly flexed
Hamstrings: Prone, neutral hip rotation
Gluteals: Side-lying with controlled pelvic position
Small changes in limb position can significantly alter echogenicity and fiber appearance. Consistency is critical - especially for follow-up scans.
Step 2: Transducer Selection Is a Clinical Decision
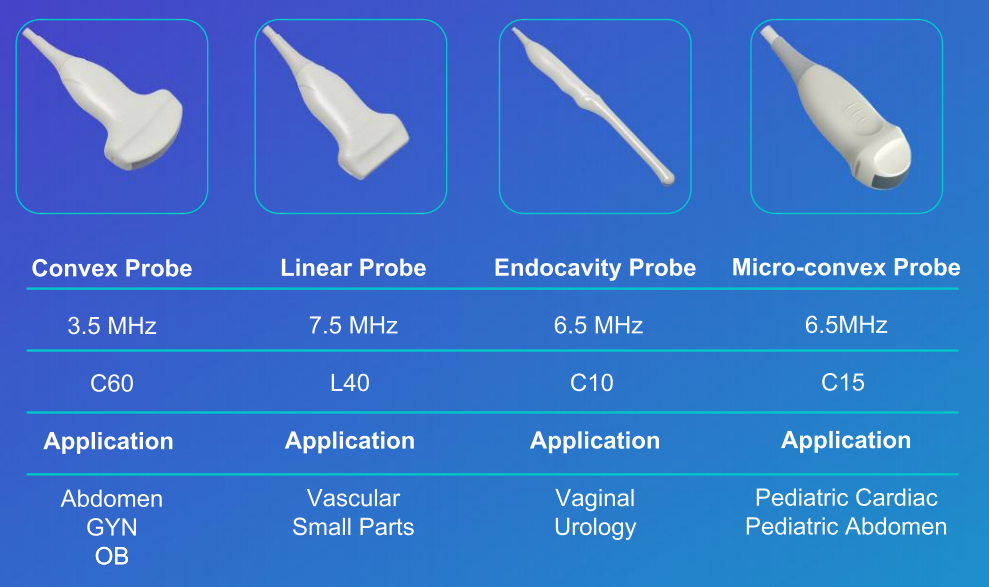
Probe choice should match the depth and target tissue, not convenience.
High-frequency linear probes for superficial muscles
Lower-frequency probes for deeper structures (e.g., gluteals, proximal thigh)
Understanding the trade-off between resolution and penetration allows clinicians to adapt scanning strategy without compromising interpretation.
Step 3: Artefact Control Is a Skill, Not a Setting
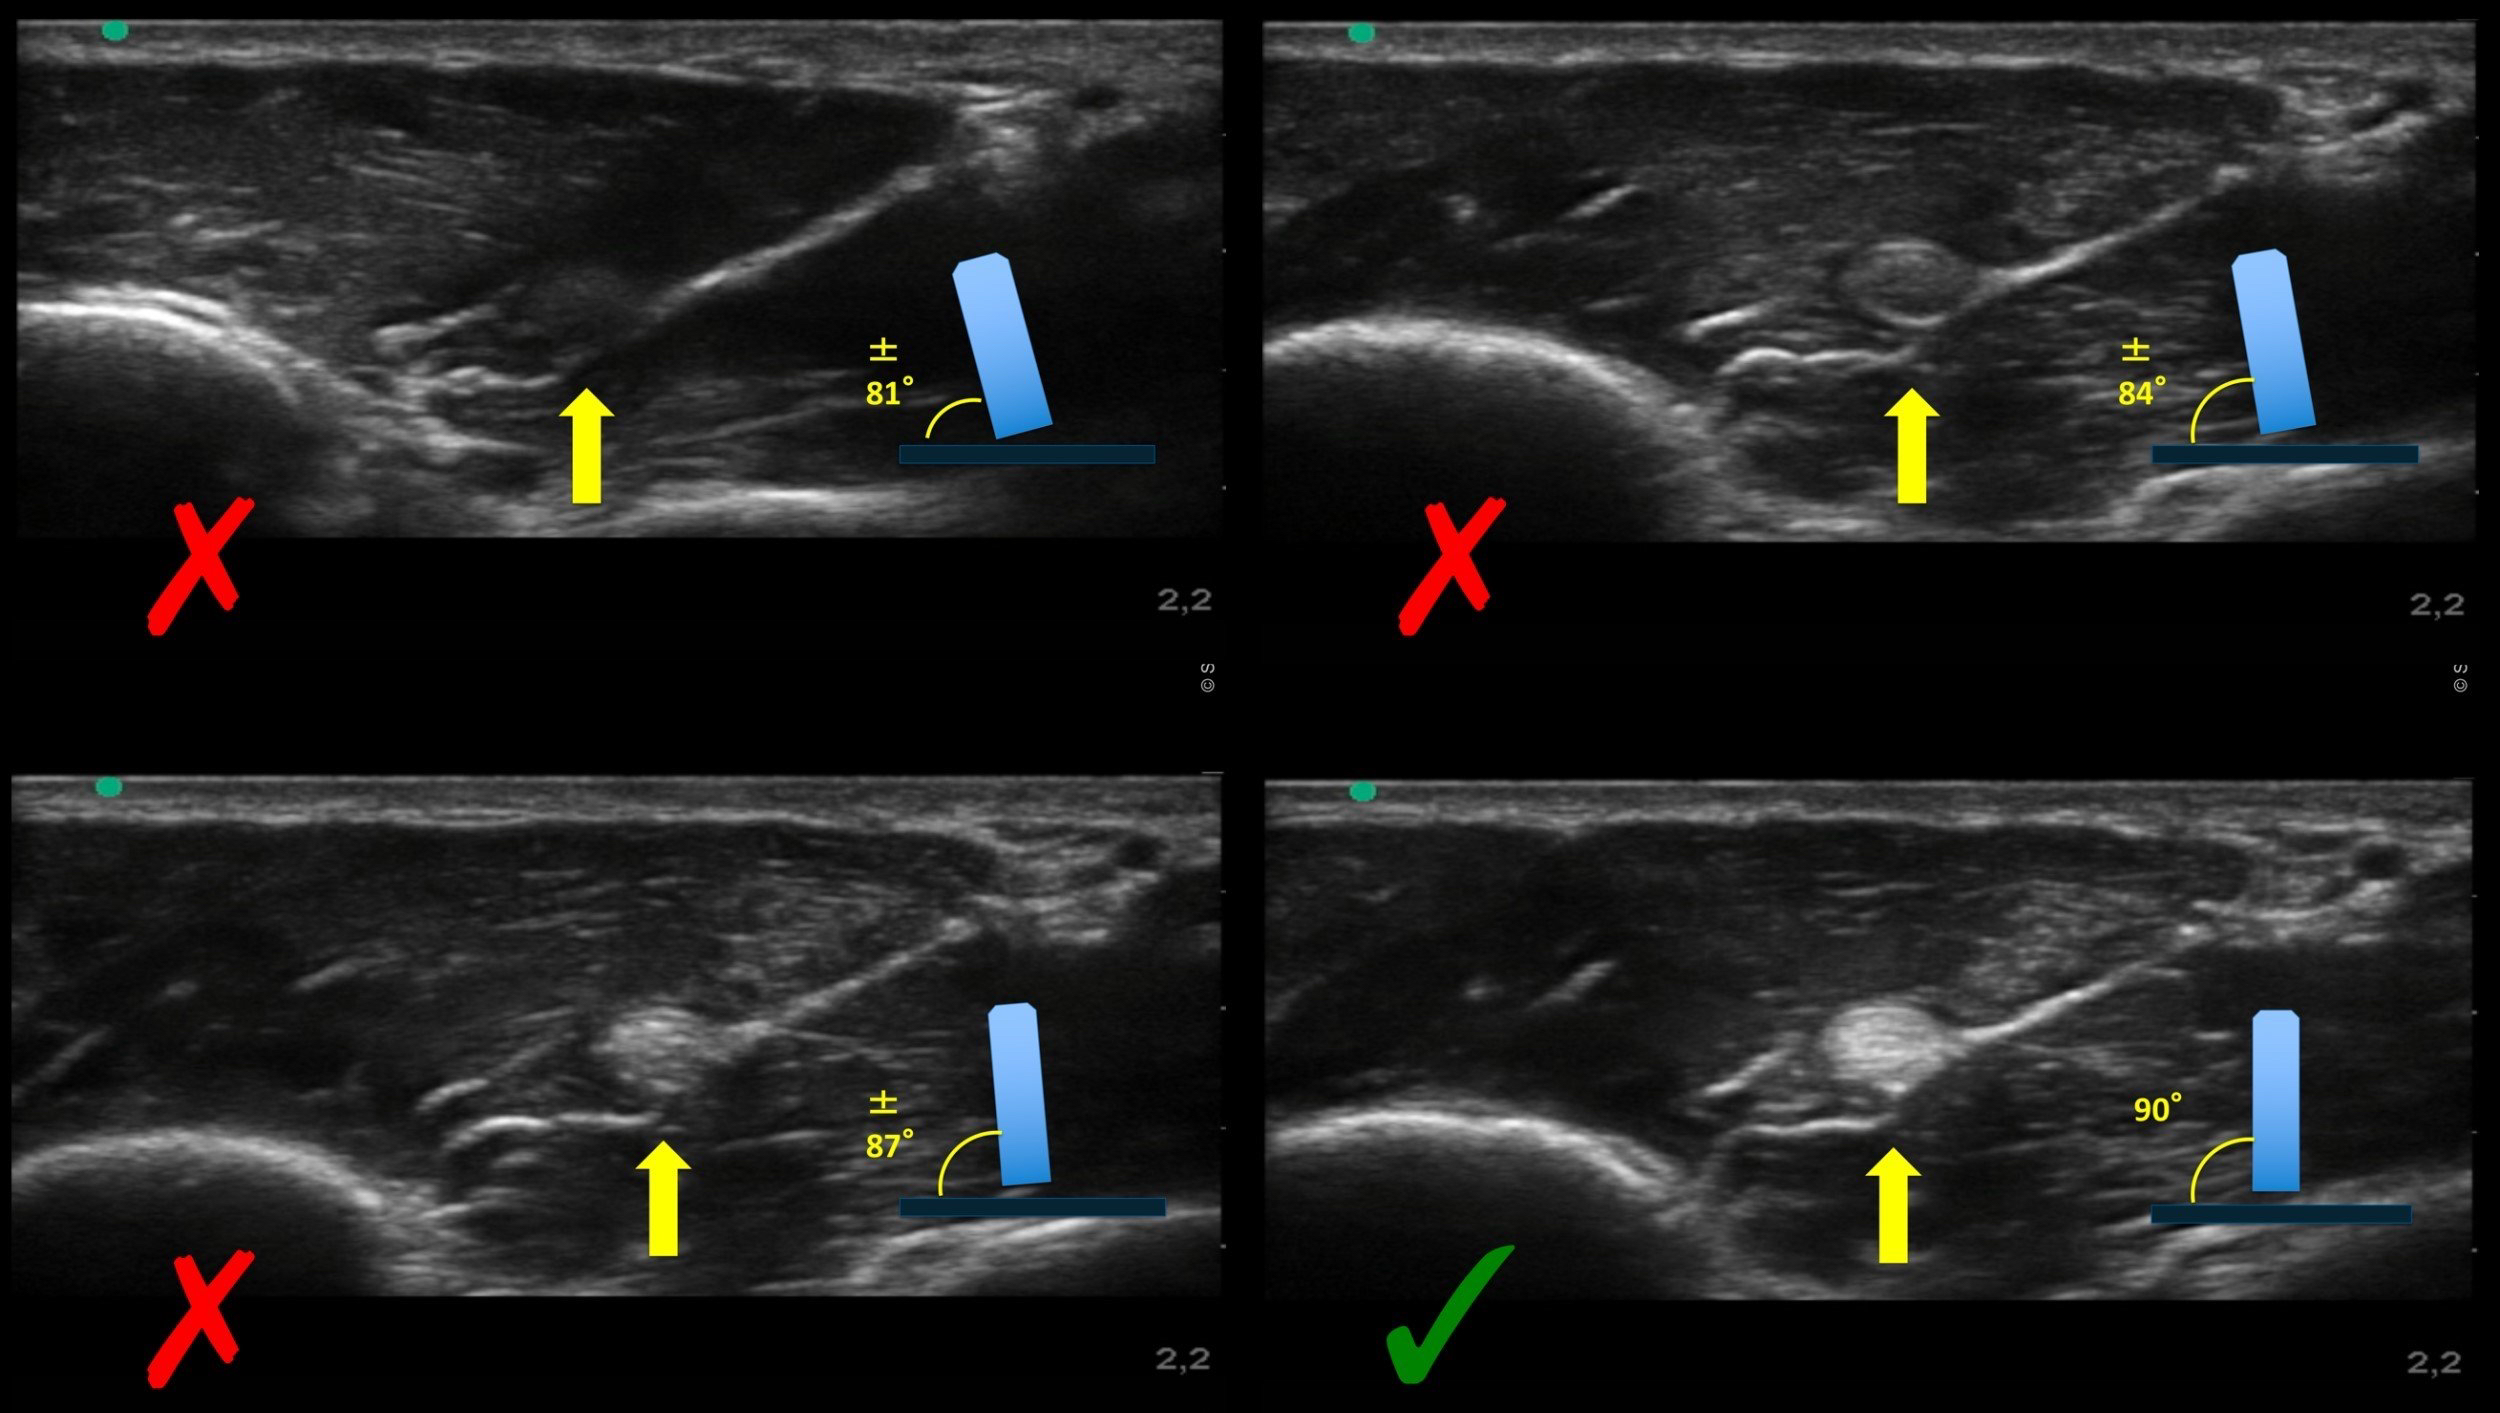
Many apparent “abnormalities” are artefacts.
Clinicians must actively manage:
Gain and depth
Focal zone placement
Probe pressure and angle
Anisotropy, especially in oblique fibers
Beam steering and angle correction are particularly important when evaluating central tendons, aponeuroses, and pennate muscle architecture.
Step 4: Transverse First, Then Longitudinal
A disciplined scan sequence matters.
Transverse views help localize pathology and assess cross-sectional symmetry
Longitudinal views evaluate fiber continuity, MTJ integrity, and tendon behavior
Echo-palpation should be used strategically to correlate symptoms with imaging findings—not to chase pain alone.
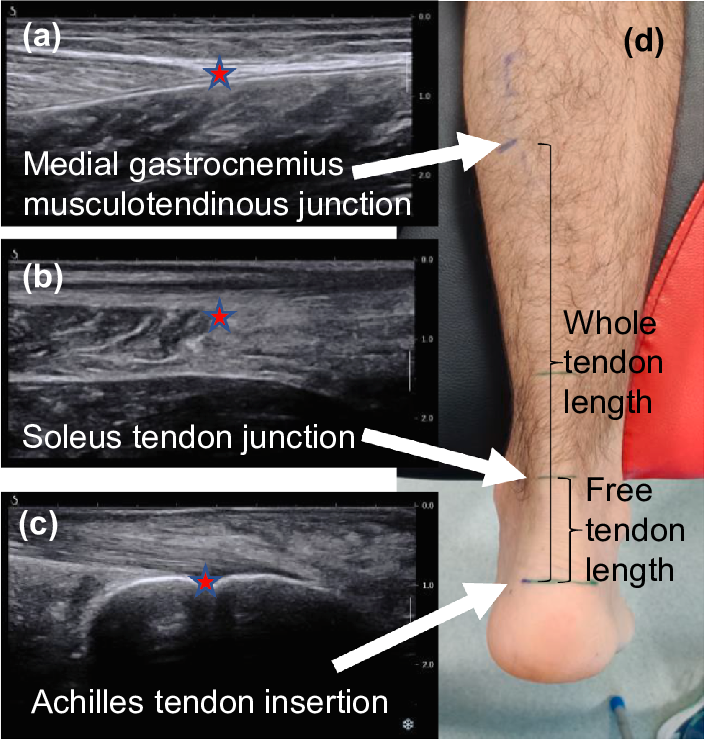
Step 5: Evaluate the Entire Muscle–Tendon Unit
Muscle injuries rarely exist in isolation.
A complete assessment includes:
Tendon insertion
Myotendinous junction (MTJ)
Muscle belly
Intramuscular aponeuroses
Clinically relevant pathology often exists proximal or distal to the patient’s reported pain.
Step 6: Dynamic Assessment Changes Everything
Static images are limited.
Dynamic ultrasound allows clinicians to observe:
Fiber glide during contraction
Gapping or delayed tension transmission
Loss of contraction symmetry
These findings directly influence:
Exercise selection
Loading progressions
Sprinting and high-speed running decisions
RTP risk stratification
Step 7: The Contralateral Side Is Your Best Control
Muscle architecture varies widely between individuals.
Comparing sides helps identify:
Subtle asymmetries
Residual remodeling
Incomplete recovery
This step is especially valuable when symptoms have resolved but performance questions remain.
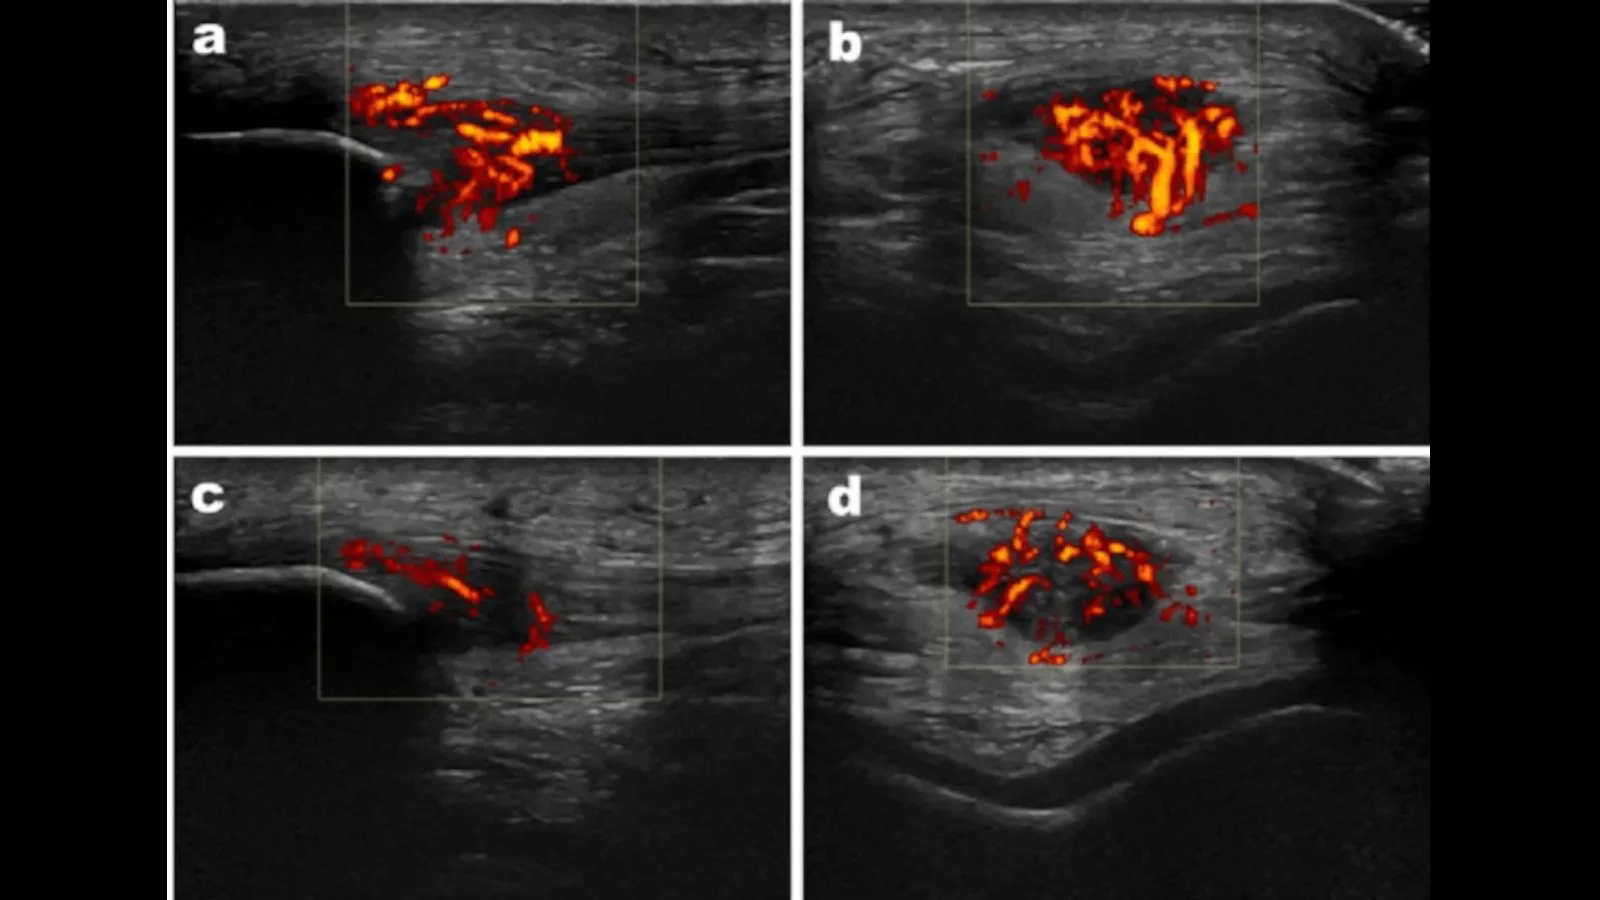
Step 8: Doppler Adds Context - Not Diagnosis
Color or power Doppler can provide insight into:
Hyperemia
Neovascularization
Ongoing inflammatory activity
However, Doppler findings should always be interpreted alongside clinical presentation, functional testing, and loading tolerance.
The Bigger Picture: Ultrasound as a Decision-Support Tool
Muscle ultrasound should not be used to “clear” or “deny” return to play.
Instead, it functions best as a contextual decision-support tool, integrated with:
Clinical exam
Performance metrics
Load history
Athlete-reported symptoms
When used this way, ultrasound enhances - not replaces - clinical reasoning.
Why We Teach Ultrasound This Way
In our diagnostic ultrasound course, we focus on:
Structured scanning frameworks
Real sport and rehab scenarios
Repeatable, defensible technique
Clinician confidence, not image perfection
Because in high-performance environments, clarity beats complexity, and process beats presets.
Final Thought
You don’t need the newest machine to be effective with ultrasound.
You need:
A systematic approach
An understanding of artefacts and anatomy
A clear reason for every scan
Muscle ultrasound is only as good as the clinician holding the probe—and the thinking behind it.