
Dry needling is widely used in musculoskeletal practice, yet the level of anatomical precision applied during intervention varies significantly. In superficial regions, palpation may be sufficient. In deep anatomical compartments, however, assumption is not the same as certainty.
Diagnostic ultrasound changes that equation.
This discussion is not about using technology for novelty. It is about anatomical verification, risk mitigation, and clinical accountability particularly when intervening near critical structures.
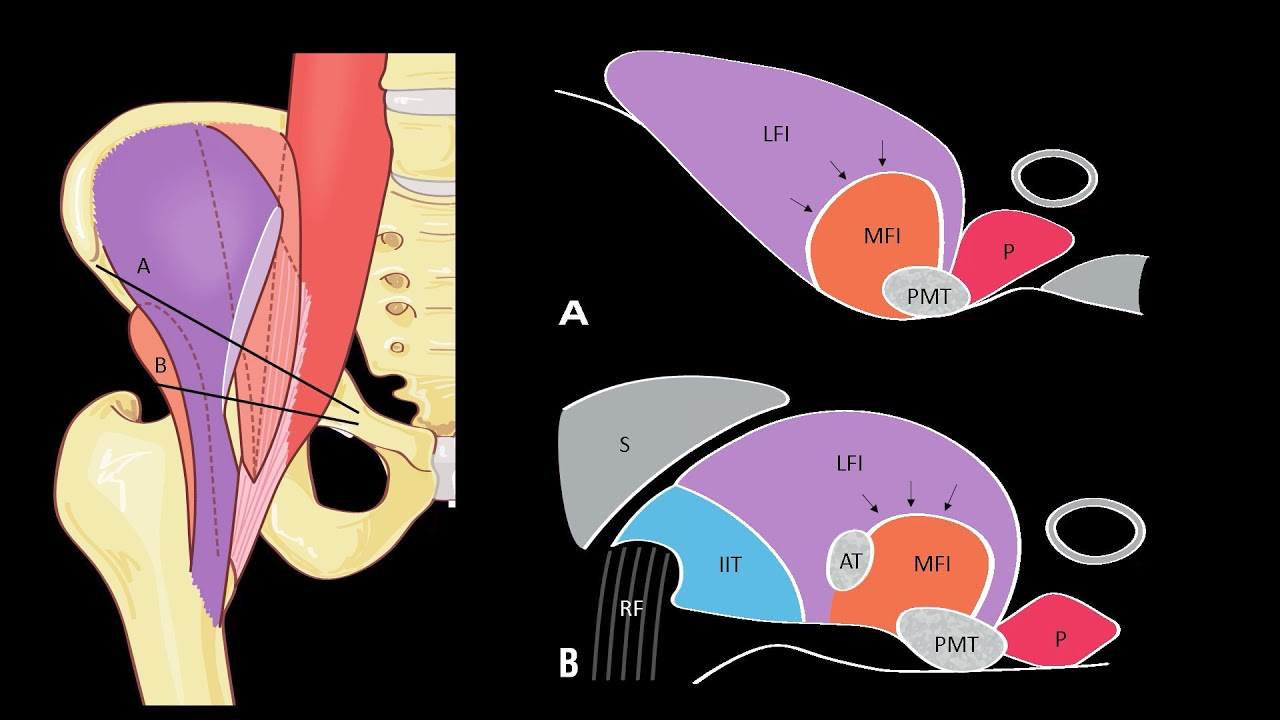
The Psoas Is a Deep, High-Consequence Structure
The psoas lies deep within the abdominal cavity, adjacent to the lumbar spine, anterior to the transverse processes, and in close proximity to abdominal viscera, the femoral nerve, and major vascular structures. Its anatomical depth varies significantly depending on body habitus, pelvic orientation, and abdominal wall thickness.
Palpation-based targeting in this region depends on estimation.
Ultrasound allows direct visualization of:
muscle borders
fascial layers
adjacent bowel
vascular structures
relative depth from the skin surface
This transforms intervention from inferred anatomy to confirmed anatomy.
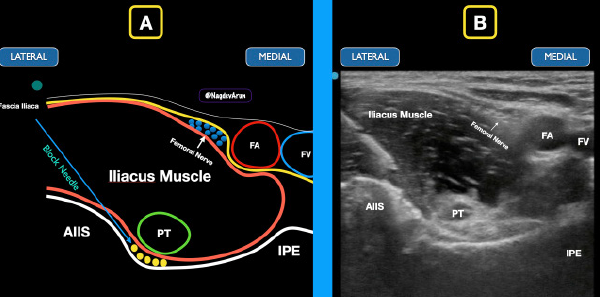
Diagnostic Confirmation Before Intervention
At an RMSK level, intervention should follow diagnostic reasoning.
Before considering dry needling of the psoas, ultrasound can assess:
muscle thickness
asymmetry compared to contralateral side
dynamic contraction
tissue echogenicity
fascial glide
This confirms whether the psoas is meaningfully involved in the clinical presentation.
Needling without imaging assumes involvement.
Needling with diagnostic confirmation strengthens the indication.
Risk Mitigation in Deep Interventions
Dry needling is often described as low risk. That description largely reflects superficial targets.
The psoas is different.
Without imaging, potential risks include:
peritoneal breach
bowel irritation
hematoma
neural irritation
Ultrasound guidance does not eliminate risk, but it substantially reduces uncertainty. Needle visualization allows confirmation of trajectory and depth in real time, ensuring that the intended tissue and only that tissue is engaged.
Diagnostic and Interventional Ultrasound Should Not Be Separated
There is a meaningful distinction between diagnostic and interventional ultrasound, yet in deep structures they should function together.
Diagnostic ultrasound determines whether intervention is appropriate.
Interventional ultrasound ensures that the intervention is precise.
When used together, the clinician moves from exploratory needling to anatomically justified treatment.
This is particularly relevant in regions where anatomical variability and proximity to vital structures elevate consequence.
Clinical Application: When Is Guidance Justified?
Ultrasound guidance is especially justified when:
the target structure is deep
critical anatomy is nearby
body habitus limits palpation accuracy
symptoms persist despite superficial intervention
prior blind needling failed
The psoas meets all of these criteria.
In such cases, ultrasound is not an accessory it is a safeguard.
A Professional Responsibility
Advanced intervention requires advanced reasoning.
Ultrasound should enhance safety and precision, not serve as a marketing differentiator.
The question is not whether dry needling “works.”
The question is whether it can be performed with the highest level of anatomical accountability.
When deep structures such as the psoas are involved, the justification for diagnostic ultrasound–guided intervention is strong.
And at RMSK-level practice, that distinction matters.
If you’re integrating dry needling into your practice, consider whether your anatomical precision matches the complexity of your targets.
Advanced regions require advanced reasoning.
Our ultrasound education and mentorship programs emphasize diagnostic clarity, dynamic assessment, and responsible interventional guidance particularly in high-consequence anatomical zones.
👉 Explore advanced MSK ultrasound education