
Most scanning mistakes aren’t “probe problems.” They’re physics problems - and they change diagnoses.
MSK ultrasound is powerful because it’s portable and real-time - but it’s also criticized as user-dependent. The difference between “seeing” and “misreading” is often whether the clinician recognizes artifacts and knows how to fix them.
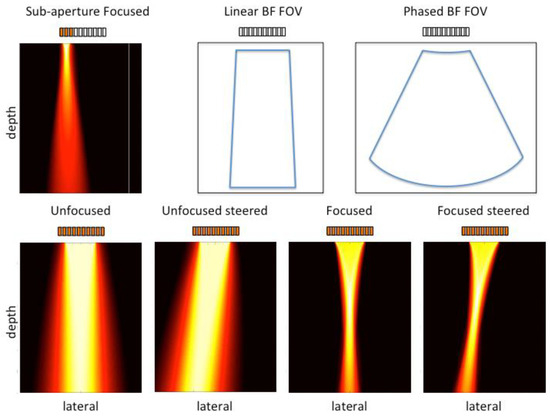
Section 1 - The uncomfortable truth: ultrasound is user-dependent
Ultrasound isn’t a camera. It’s an echo-based reconstruction. The machine is making assumptions about how sound travels, where echoes came from, and what they mean. When those assumptions get violated, artifacts appear - and those artifacts can mimic pathology.

Section 2 - Physics isn’t “extra”: it’s interpretation protection
Most clinicians learn:
probe handling
anatomy recognition
a few classic pathologies
But many courses underteach the machine-setting → beam-behavior → artifact → interpretation chain.
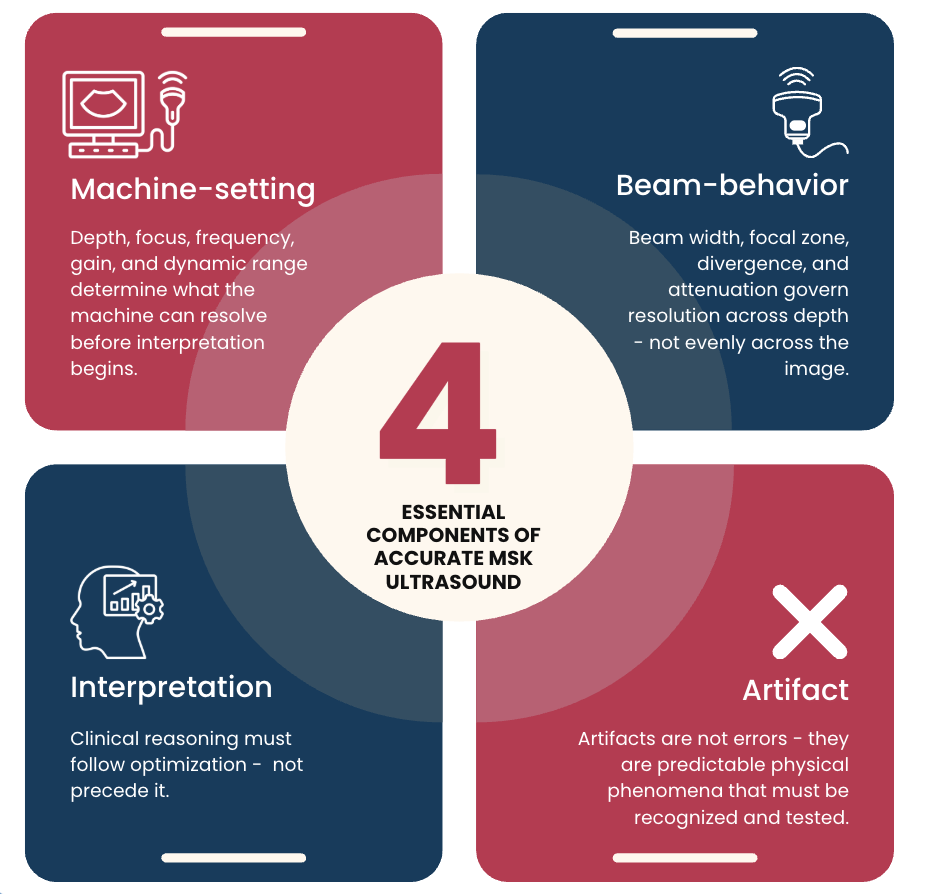
This review breaks artifacts into mechanisms that show up constantly in MSK scanning, including:
focal zone / beam width issues
attenuation-related phenomena
beam path issues (reverberation, mirror)
side lobes / grating lobes
speed-of-sound effects (refraction)
range ambiguity (“ghost objects”)

Section 3 - The “artifact loop” clinicians should run in real time
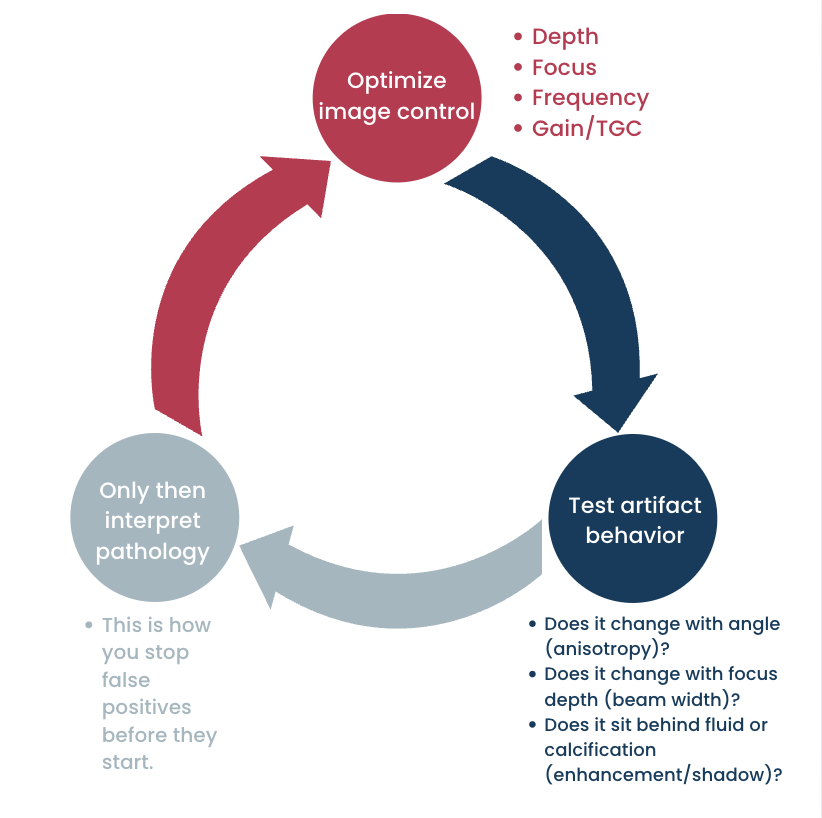
Instead of “I see something abnormal,” use this rapid loop:
Optimize image control
Depth
Focus
Frequency
Gain/TGC
Test artifact behavior
Does it change with angle (anisotropy)?
Does it change with focus depth (beam width)?
Does it sit behind fluid or calcification (enhancement/shadow)?
Does it duplicate across bone (mirror)?
Only then interpret pathology
This is how you stop false positives before they start.
Section 4 - Why this matters in sports medicine (RMSK lens)
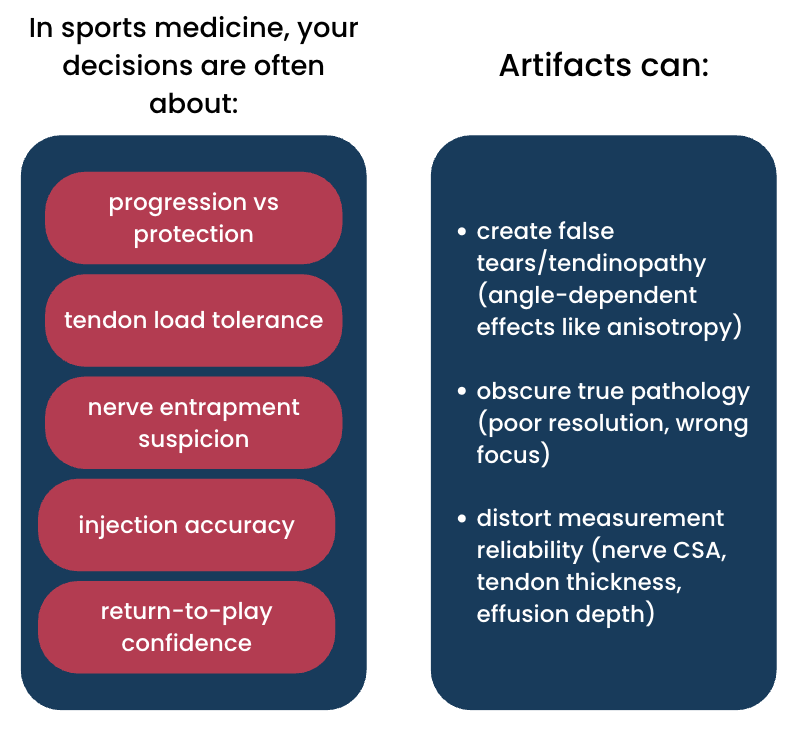
In sports medicine, your decisions are often about:
progression vs protection
tendon load tolerance
nerve entrapment suspicion
injection accuracy
return-to-play confidence
Artifacts can:
create false tears/tendinopathy (angle-dependent effects like anisotropy)
obscure true pathology (poor resolution, wrong focus)
distort measurement reliability (nerve CSA, tendon thickness, effusion depth)
This is why physics belongs in the “clinical skill” category, not the “optional module” category.
Section 5 - What this blog series will cover next
Image Control (how to prevent artifacts)
Depth: why “too deep” reduces usable resolution
Focus / Beam width: why lateral resolution only peaks at the focal zone
Frequency: resolution vs penetration and why your image gets noisy
Interpretation Protection (how not to misdiagnose artifacts)
Anisotropy: the #1 tendon trap
Posterior enhancement & shadowing: fluid vs calcification clues
Reverberation & ring-down: needles, metal, gas, and “comet tails”
Mirror image: bony interfaces duplicating anatomy
Side lobes: “ghost echoes” inside cysts
Refraction / speed-of-sound: why needles look bent
Range ambiguity: “false septations” in large cysts
Want to scan with more confidence?
We teach ultrasound the way RMSK clinicians actually use it: image optimization, artifact recognition, dynamic scanning, and clinical integration - not just anatomy screenshots.