
What Musculoskeletal Ultrasound Can Reveal
In clinical practice, we often assume the sciatic nerve follows a predictable course beneath the piriformis muscle.
Most of the time, that assumption is correct.
But not always.
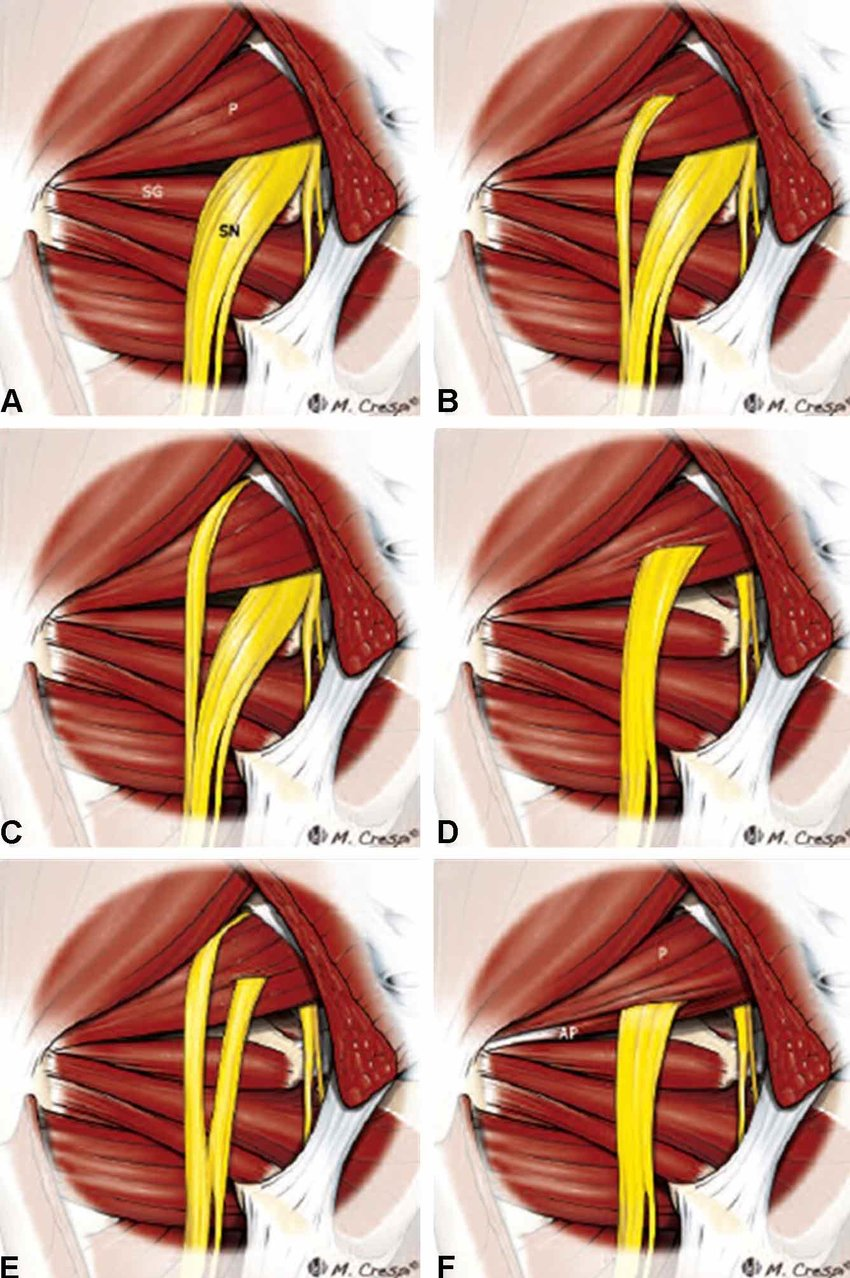
Large cadaveric analyses show that sciatic nerve–piriformis anatomical variants occur in roughly 13–17% of individuals, meaning clinicians will encounter these variations regularly in sports medicine, rehabilitation, and interventional procedures.
Understanding these variants is more than an academic exercise.
It directly affects:
• diagnostic reasoning
• ultrasound interpretation
• injection safety
• surgical planning
Musculoskeletal ultrasound offers a powerful way to visualize these relationships dynamically at the point of care.
The Classic Classification: Beaton & Anson
Variant (Beaton & Anson) | Anatomic relationship | Prevalence (best evidence) | Reported range (cadaveric examples) | Key sonographic signs to document | Clinical relevance (what it changes) |
Type A | Undivided SN below PM | ~90% pooled | Type A varies ~64.5–100% across included studies | Single trunk deep to PM; no early branching; stable “below PM corridor” | Baseline “expected” anatomy; still document to prevent assumption |
Type B | FN through PM; TN below | ~8% pooled | FN/TN division may be high; type B rates can exceed 20–30% in some East Asian cadaveric series | Early division + FN tracked intramuscularly; TN remains deep/ inferior; cine if dynamic compression suspected | Procedural hazard zone; higher risk of incomplete “sciatic block”; relevant for injection targeting |
Type C | FN above PM; TN below | ~2% pooled | Reported up to ~10% in some series | Early division; FN more superior/ superficial; TN below; track both branches | Same “high bifurcation” issues (block/ injection/ surgery) |
Type D | Undivided SN through PM | ~1% pooled | Reported up to ~8–10% in smaller series | SN clearly courses within PM fibers (intramuscular) in oblique view; document bilaterality when present | High relevance for needle safety; plausible mechanical entrapment pattern under load/rotation |
Type E | FN above; TN through | Not pooled in 2020 meta- analysis | Rare; reported in small cadaveric series (e.g., ~1–5% in some small samples) | Two branches; TN intramuscular; FN above PM; requires careful branch tracking | Potentially high procedural relevance; evidence base for clinical correlation is limited (note as such) |
Type F | Undivided SN above PM | Not pooled in 2020 meta- analysis | Rare; reported in small series (e.g., ~0.3–5% depending on sample) | Nerve not in expected deep-to- PM corridor; confirm identity by fascicles + tracking | High procedural relevance (avoid “assuming below PM”); clinical correlation data limited |
Why These Variants Matter Clinically
One of the most important takeaways from the anatomical literature is this:
Variant anatomy does not automatically mean pathology.
Many individuals with sciatic nerve variants have no symptoms at all.
However, variants can influence:
• deep gluteal pain presentations
• nerve compression patterns
• response to injections
• outcomes of sciatic nerve blocks
For clinicians performing procedures, this becomes especially important.
Assuming the nerve always lies below piriformis can occasionally place needles in the wrong location.
What Ultrasound Can and Cannot Show
Musculoskeletal ultrasound cannot visualize the intrapelvic origin of the sciatic nerve.
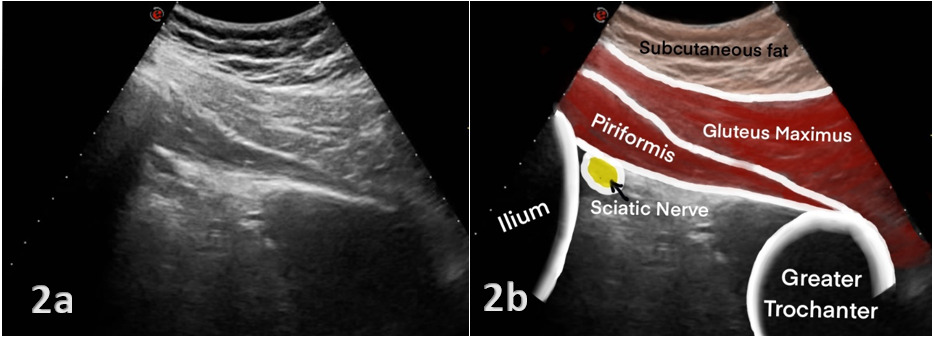
However, it can reliably evaluate the extrapelvic relationship between the sciatic nerve and piriformis in the deep gluteal region.
This includes:
• identifying early nerve division
• tracking tibial and fibular branches
• visualizing nerve course relative to piriformis fibers
• guiding injections safely
Ultrasound also allows dynamic assessment, something static imaging cannot provide.
Normal Sonographic Appearance of the Sciatic Nerve
Recognizing normal nerve structure is essential before interpreting variants.
On ultrasound:
Short-axis view
The nerve displays a honeycomb pattern, with hypoechoic fascicles separated by hyperechoic connective tissue septae.
Long-axis view
The nerve resembles a bundle of parallel fascicles, often described as a “bundle of straws.”
These features help confirm that the structure being visualized is truly a peripheral nerve.
RMSK-Level Ultrasound Scanning Protocol
Dynamic Maneuvers That Improve Visualization
Several movement strategies can improve the clarity of deep gluteal structures.
Two particularly useful maneuvers include:
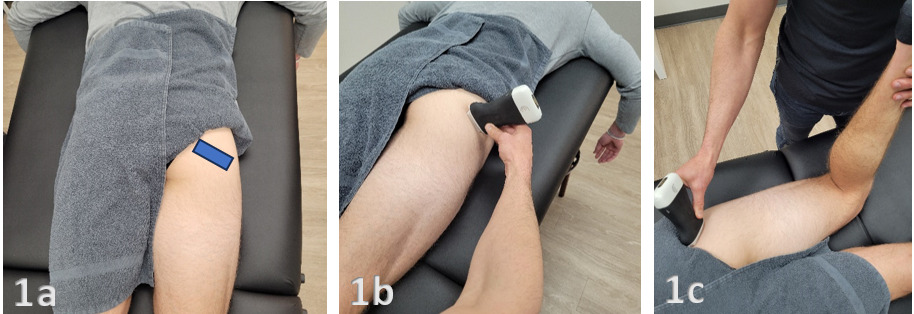
Hip rotation with the knee flexed to ~90°
Passive internal and external rotation can help isolate piriformis beneath the gluteus maximus.
Hip adduction and abduction
These movements can shift soft tissue layers and improve visualization of the nerve relative to piriformis.
Dynamic scanning also helps differentiate artifact from true anatomical relationships.
Common Pitfalls When Scanning the Deep Gluteal Region
Even experienced clinicians encounter challenges when imaging this region.
Depth and Attenuation
The piriformis muscle lies beneath the gluteus maximus, which increases imaging depth and reduces resolution.
Anisotropy
Peripheral nerves are susceptible to anisotropy.
If the probe is not perpendicular to the nerve, it may appear falsely hypoechoic.
Structure Misidentification
Gluteus maximus can sometimes be mistaken for piriformis when scanning depth is not optimized.
Dynamic scanning can help clarify this relationship.
Practical Takeaway for Clinicians
Sciatic nerve–piriformis variants are not rare.
Understanding these relationships improves:
• diagnostic reasoning
• procedural safety
• interpretation of ultrasound imaging
Musculoskeletal ultrasound offers a powerful tool to visualize these variants dynamically and guide clinical decision-making.
For clinicians working with athletes or active populations, developing a structured posterior hip ultrasound protocol can dramatically improve both accuracy and confidence.
References
Poutoglidou F et al.
Sciatic Nerve Variants and the Piriformis Muscle: A Systematic Review and Meta-Analysis.
Smoll NR.
Variations of the piriformis and sciatic nerve with clinical consequence.
Manske RC et al.
Use of Diagnostic Musculoskeletal Ultrasound in the Evaluation of Piriformis Syndrome.